Categories
Blog

Sleep Science Isn’t About Perfect Nights—It’s About Your Mental Load

The Sleep Crisis Is Quietly Destroying Your Mental Health

More than one in three American adults isn’t getting seven hours of sleep. That’s not just a statistic. That’s your coworker running on fumes. That’s you reaching for your third coffee by 10 AM. That’s the slow accumulation of decisions not made, emotions not processed, and resilience not built.

Sleep Science Isn't About Perfect Nights—It's About Your Mental Load
Sleep Science Isn’t About Perfect Nights—It’s About Your Mental Load

The economy feels this too. We’re talking about 411 billion dollars in lost productivity annually—money that represents real human capacity slipping away, night after night. But here’s what the headlines miss: the productivity loss is just the symptom. The actual problem lives in your nervous system. Sleep deprivation doesn’t just make you slower. It makes you more anxious, more reactive, and harder on yourself.

When you’re sleep-deprived, your amygdala, the part of your brain that processes fear and emotional intensity, becomes hyperactive. Everything feels more threatening. A critical email feels personal. A small mistake feels catastrophic. Your prefrontal cortex, the rational part that usually keeps things in perspective, is offline. This is why people in chronic sleep debt often struggle with mental health challenges that feel mysteriously resistant to other interventions.

Illustration for Sleep Science Isn't About Perfect Nights—It's About Your Mental Load
Illustration for Sleep Science Isn’t About Perfect Nights—It’s About Your Mental Load

Why the High Performance Movement Got Sleep Right (And What It’s Missing)

Matthew Walker’s “Why We Sleep” did something remarkable when it landed in 2017. It gave us permission to treat sleep like a performance variable instead of a luxury. Suddenly, CEOs and athletes and ambitious people everywhere weren’t indulgent for prioritizing rest. They were strategic. That shift mattered. It still matters.

The data-driven sleep optimization wave that followed, Oura Rings tracking your HRV, WHOOP bands monitoring your recovery, apps quantifying your sleep architecture, created a framework where you can actually see what’s happening in your body. Knowledge is powerful. Seeing your own data removes the guesswork. It validates that yes, those three late nights did accumulate into a measurable recovery deficit.

But here’s what sometimes gets lost in optimization culture: tracking everything can become another form of mental load. Obsessing over sleep scores. Feeling guilty when your recovery isn’t optimal. Treating your body like a machine that should perform consistently instead of like a living system with legitimate rhythms and needs. The performance approach works best when it’s paired with self-compassion, not perfectionistic demands.

Your Chronotype Isn’t a Character Flaw—It’s Your Biology Speaking

Chronobiology research keeps confirming something your gut already knew: people have genuinely different sleep timing preferences. Some of us are wired to wake at 5 AM naturally energized. Others need that 8:30 AM start to function like humans. Neither is better. Neither is lazier. It’s just how your individual circadian system is organized.

This matters emotionally because so many of us have internalized the message that early rising equals productivity and discipline. If you’re someone whose natural rhythm peaks at 10 PM, fighting that every day creates chronic low-level stress on your nervous system. You’re not failing at mornings. Your brain chemistry just works differently.

Huberman Lab sleep protocols go deep into the chronobiology science and offer frameworks for working with your natural timing rather than against it. The goal isn’t to become an early riser if that’s not your biology. The goal is to understand your pattern and build a life structure that supports it.

The Tools That Actually Help (And Why Context Matters)

Red light therapy and weighted blankets have moved from wellness fringes into legitimate sleep support categories, and the research backing them keeps growing. Red light wavelengths genuinely signal your body toward melatonin production. The gentle pressure of weighted blankets activates your parasympathetic nervous system. These aren’t placebos, though believing in them probably helps too.

But here’s the honest truth: a tool only works when it addresses an actual barrier. If your sleep environment is chaotic, a weighted blanket won’t solve it. If your nervous system is flooded with caffeine and cortisol, red light therapy is working against the current. The real question is what your particular barrier actually is.

Is it that your mind won’t quiet? Then you need nervous system regulation before you need better sleep architecture. Is it that your body never feels settled? Then weighted input might be genuinely transformative. Is it that light exposure is disrupting your circadian rhythm? Red light therapy actually makes sense.

Sleep Foundation research offers evidence-based starting points for evaluating what interventions match your specific situation rather than just following what’s trending.

Building Sleep as Mental Load Management, Not Just Sleep Optimization

The highest-performing humans don’t think of sleep as recovery time separated from their real life. They think of it as foundational mental load management. When your sleep is solid, everything else becomes more manageable. You make better decisions. You’re kinder to people you love. You handle stress without spiraling.

This reframe takes pressure off sleep itself. You’re not trying to achieve a perfect sleep score. You’re trying to create conditions where your nervous system can actually rest so you have the emotional capacity for your actual life. That’s the whole point.

Start where you are. Maybe it’s blocking out your bedroom. Maybe it’s examining your caffeine timing. Maybe it’s working with a chronotype that actually matches your biology instead of fighting it. Maybe it’s adding weighted pressure or red light. The specific tool matters less than the intention: you’re building a life where sleep is genuinely possible, not squeezed in around everything else.

What’s one barrier to sleep that’s been nagging at you? The one you keep thinking you should fix but haven’t quite addressed? That’s your starting point. Share it in the comments if you want. Sometimes just naming it is the first step toward changing it.

Categories
Blog

The Ultra-Processed Food Debate Just Got Louder: What the NOVA Classification Controversy in 2025 Means for Your Grocery Cart

The Numbers Are Getting Harder to Ignore

Let’s start with what the research is actually showing. A major 2025 meta-analysis tracking over 9.9 million people found that those eating the most ultra-processed foods faced a 50% higher risk of dying from cardiovascular disease. Fifty percent. Not a small bump. Not statistical noise. The same study flagged a 12% increased risk for type 2 diabetes. These aren’t marginal findings. They’re the kind of numbers that make public health officials sit up straighter.

Here’s what makes this moment different: we’re not just seeing one study or even a handful of studies anymore. We’re seeing the weight of evidence become genuinely hard to dismiss. The BMJ Ultra-Processed Food Meta-Analysis pulled together decades of data. That’s not an opinion. That’s a pattern.

But here’s where it gets complicated. An NIH-funded study in 2025 revealed that Americans are still getting roughly 57% of their daily calories from ultra-processed foods. That number has barely budged despite years of dietary guidelines, nutrition education, and wellness trends. We’re stuck. And now the scientific community is fighting about why we’re stuck and what we should even be measuring.

The NOVA System Is Under Attack, and That’s Actually Revealing

The NOVA classification system was designed to cut through the noise. Brazilian researcher Carlos Monteiro created it in the early 2000s to sort foods into four categories: unprocessed or minimally processed, processed culinary ingredients, processed foods, and ultra-processed foods. Simple. Clean. It became the backbone of a lot of global health recommendations.

Then 2025 happened. The International Food Information Council, which represents food manufacturers and related industries, published a white paper arguing that NOVA’s categories are too broad and scientifically inconsistent. They’re not entirely wrong. The system does lump together a shocking variety of products under “ultra-processed.” A can of low-sodium beans might share the same classification as a neon-colored energy drink. A whole-grain bread with one synthetic preservative sits in the same bucket as a heavily sweetened cereal.

But the fact that NOVA is getting criticized doesn’t mean the underlying concern is wrong. It means we need better definitions, not that we should abandon the concept entirely. The debate is actually proof that we’re finally taking this seriously enough to argue about the details.

What “Healthy” Actually Means Is Still Up for Grabs

The FDA proposed new draft guidance in 2025 for what qualifies as “healthy” on a food label. If you were hoping this would finally crack the code on ultra-processing, prepare to feel disappointed. Critics quickly pointed out that the FDA’s framework still doesn’t meaningfully address ultra-processing as its own distinct category. It focuses on nutrients: sodium, sugar, saturated fat. Those matter. But they don’t tell you about the manufacturing process, the degree of transformation, or the structural changes to the food itself.

You can have a product that hits all the FDA’s nutrient targets and still be fundamentally ultra-processed. That’s not a flaw in your understanding. That’s an actual gap in policy. Check out FDA Healthy Food Labeling Guidance if you want to see how they’re defining it now. Then ask yourself whether that definition actually addresses your concerns.

This matters because marketing has gotten very, very good. Brands know exactly what you’re worried about. So they reformulate just enough to check the right boxes.

The “Cleaner” Label Problem Is Bigger Than You Think

In 2025, independent food researchers took a close look at products like Halo Top ice cream and Kind Bars. These are brands that built their reputation on being different. Better ingredients. Simpler formulas. Less processed. Great story. Except when researchers analyzed them, most still landed squarely in NOVA’s Group 4 ultra-processed category. The clean labels were real. The cleaner ingredients were often real. But the fundamental processing remained.

This isn’t to say these products are worthless or that choosing them over conventional alternatives is pointless. Ingredient quality and degree of processing just aren’t the same thing. You can have excellent ingredients that are processed beyond recognition. You can have foods with minimal additives that have still been industrially engineered to maximize shelf stability, texture, and profit margins.

What matters most is that you see this clearly. Not to make you feel bad about past choices, but so your future choices can be based on what you actually want. If you prefer whole foods when possible, that’s useful information. If convenience sometimes wins, that’s also real life. Just know what you’re choosing and why.

What You Can Actually Do With This Information

The current debate isn’t a reason to panic or assume every guideline is garbage. It’s an invitation to think probabilistically about your own eating. That 57% figure tracking ultra-processed foods doesn’t mean you need to get to zero. It means there’s room to shift the ratio. Even small movements create measurable health outcomes.

Start with visibility. Spend one week just noticing what percentage of your food falls into NOVA Group 4. You don’t have to change anything yet. Just pay attention. Look at what’s grabbing your calories. Then ask yourself: which of these do I actually want, and which am I eating because it’s convenient, it’s what’s available, or it’s what I’ve always done?

From there, look for the easiest trades. Not the most restrictive version of yourself, but real substitutions that work for your life. Maybe it’s swapping one ultra-processed snack for something minimally processed. Maybe it’s cooking one additional meal per week. Maybe it’s adjusting your grocery shopping pattern so whole foods are the first thing you grab, not the third.

The science is getting louder. The definitions are getting debated. The marketing is getting smarter. You get to be smarter too. What patterns have you noticed in your own food choices? What single change would be easiest to implement? Drop a comment below if you want to talk through your specific situation.

Categories
Blog

Magnesium L-Threonate and Brain Health: What the 2025 Research Actually Shows

The Magnesium Moment We’re Actually Having

Let’s be honest. Magnesium is trending harder than it has in years. Search interest in “magnesium for sleep” has skyrocketed 340% since early 2024. Your Instagram feed probably features at least three people talking about their magnesium glycinate routine. There’s a magnesium supplement in nearly every wellness influencer’s daily stack.

But here’s what’s interesting: beneath all the noise, something legitimately compelling is happening in the neuroscience literature. A new form called magnesium L-threonate is generating research that actually warrants paying attention to. Not because it’s a miracle cure, and not because you should overhaul your entire supplement protocol based on hype. The mechanism is specific, the recent data is solid, and the question it answers is genuinely important: can we improve cognitive function in aging brains?

That’s worth understanding. So let’s dig into what the evidence actually says.

Why Magnesium L-Threonate Is Different (And Why That Matters)

Most magnesium supplements don’t make it to your brain. This isn’t a failure of the supplement. It’s biology. Your blood-brain barrier is extraordinarily selective about what enters your central nervous system. Think of it as a bouncer at an exclusive club, and standard magnesium forms like oxide or citrate simply don’t have the right credentials to get past it.

Magnesium L-threonate was designed to solve this problem. Researchers at MIT discovered back in 2010 that this particular form could cross the blood-brain barrier more efficiently than other magnesium compounds. The mechanism involves a specific transporter system that recognizes and preferentially moves L-threonate across that critical barrier. This wasn’t theoretical speculation. It was demonstrated in controlled research published in Neuron Journal – Magnesium and Synaptic Plasticity Research.

What’s new is that we’re finally getting rigorous follow-up trials in humans. A 2025 randomized controlled trial tracked adults aged 50 to 70 over 12 weeks. The results showed that magnesium L-threonate supplementation improved synaptic density markers by approximately 15% compared to placebo. Synaptic density matters because it’s linked to cognitive reserve, learning capacity, and protection against age-related decline.

Does this mean you should immediately start taking it? Not necessarily. But it does mean the biochemistry isn’t wishful thinking. The form was intentionally engineered for brain delivery, and we’re now seeing evidence that it works.

The Big Picture: Most of Us Are Actually Deficient

Before we get too excited about the fancy form, let’s acknowledge a baseline problem. Nearly half of all Americans don’t meet the daily recommended magnesium intake. According to recent data from the National Health and Nutrition Examination Survey, about 48% of the population falls short of the 310 to 420 milligrams daily recommendation depending on age and sex.

This matters because magnesium is involved in hundreds of enzymatic reactions. It’s essential for muscle function, nerve signaling, energy production, and bone health. Most people don’t notice a glaring deficiency because magnesium shortfalls tend to accumulate quietly. You might experience poor sleep, muscle tension, or difficulty managing stress without ever connecting it to suboptimal magnesium status.

The cognitive research is exciting, but worth noting: if you’re not meeting basic magnesium needs through diet or supplementation, that’s the first problem to solve. Getting enough magnesium from food or a standard supplement is still the foundation. The specialized forms like L-threonate are an upgrade to consider once you’ve covered the basics.

What the Latest Research Actually Says (And What It Doesn’t)

The 2025 study showing improvements in synaptic density markers is encouraging. It’s also specifically about a 12-week intervention in people aged 50 to 70. That’s a relatively narrow population and a relatively short timeframe. We don’t yet have data on whether these benefits persist over months or years, and we don’t have robust data across younger adults or across different cognitive domains beyond the specific markers measured.

The NIH Office of Dietary Supplements updated its magnesium fact sheet in 2025 to acknowledge this emerging cognitive research. But they were careful with their language. They noted that while the data is promising, larger trials are still needed before clinical recommendations change. This is exactly the right position to take. Evidence-first without overstating certainty.

That said, evidence-first doesn’t mean dismissive. The 15% improvement in synaptic density markers in a randomized controlled trial is a real finding. It suggests that magnesium L-threonate can influence brain physiology in measurable ways. For people dealing with cognitive concerns, particularly in the 50-plus age range, this research creates a reasonable case for consideration.

You can read the updated information yourself at the NIH Office of Dietary Supplements – Magnesium Fact Sheet. They’ve organized the research clearly and labeled what remains uncertain.

Making a Personal Decision (Without Waiting for Perfection)

Here’s what I think matters: perfection is the enemy of progress. We’ll never have a study so comprehensive that it answers every possible question about magnesium L-threonate. We could wait for decade-long trials across multiple populations. Or we could acknowledge what we know now, what we don’t know, and decide accordingly.

If you’re experiencing cognitive concerns, sleep issues, or age-related mental sharpness, the basic magnesium research alone makes a strong case for addressing any deficiency. If you decide magnesium L-threonate specifically is worth trying, the emerging brain-specific research gives you a rational basis for that choice. Twelve weeks is a reasonable trial period to see if you notice any personal benefit.

If you’re young with no cognitive concerns, you’re probably fine focusing on getting adequate magnesium from food and standard forms first.

The point is: this research invites thoughtful consideration, not blind enthusiasm. What matters most is that you’re actually thinking about your micronutrient status, paying attention to sleep and brain health, and willing to try evidence-informed strategies. Have you noticed any personal differences with magnesium supplementation? I’d genuinely like to hear what you’ve experienced.

Categories
Blog

Protein Cycling in 2025: What the Longevity Science Actually Says (and What You Really Need to Know)

The Buzz Around Protein Cycling and Why Your Feed Won’t Stop Talking About It

If you’ve scrolled through wellness spaces lately, you’ve probably seen protein cycling mentioned alongside words like “autophagy,” “cellular rejuvenation,” and “the future of longevity.” The basic idea sounds almost elegant: instead of eating the same amount of protein every single day, you alternate between higher and lower protein intake to trigger your body’s natural cleanup mechanisms. It’s gotten real attention, too. L-Nutra, the company behind ProLon fasting-mimicking diet programs, saw their U.S. sales jump by 340 percent between January 2024 and January 2025, with longevity research cited as the primary driver.

But here’s what I want to say upfront: just because something is trending doesn’t mean it’s straightforward. Protein cycling has legitimate research backing parts of it. It also has legitimate questions still hovering around it. And that gap between what we know and what we don’t know? That’s actually where your mental load comes in—because figuring out whether this applies to you shouldn’t require a PhD or feel like another optimization chore on an already overwhelming plate.

The Research: What Longevity Scientists Are Actually Studying

Dr. Valter Longo from USC’s Longevity Institute has been central to this conversation. His updated 2025 research on fasting-mimicking diets brought protein cycling into the mainstream spotlight by exploring how periodic reductions in protein intake might activate autophagy—essentially your cells’ recycling program. When you give your body less protein for short periods, the theory goes, it triggers the cleanup of damaged cellular components instead of constantly building new ones.

Recent data supports parts of this. A 2025 study published in Cell Metabolism journal on autophagy and nutrition found that healthy adults who ate low-protein days (under 0.4 grams per kilogram of body weight) showed measurable autophagy markers within 24 hours. That’s not nothing. Your cells actually appeared to shift into cleanup mode relatively quickly. If you weigh 150 pounds, that’s roughly 27 grams of protein or less on those days—basically like eating one palm-sized portion of chicken and calling it a day.

What makes USC Longevity Institute research on diet and aging compelling is that it’s not fixated on a single marker. They’re looking at how these patterns affect inflammation, metabolic health, and aging processes over time. The signals are real. The question is whether they translate to meaningful differences in how long you live or how well you age—and that’s where the honest gaps show up.

The Protein Numbers Game: Understanding What Your Body Actually Needs

Before diving into cycling, let’s anchor on baseline needs because this matters for your actual situation. The standard recommendation hasn’t changed: 0.8 grams of protein per kilogram of body weight daily for sedentary adults. But here’s what’s new—researchers presenting at the 2025 American Society for Nutrition conference found that active adults over 40 may genuinely benefit from 1.2 to 1.6 grams per kilogram instead. That’s a significant difference, especially if you’re strength training or trying to maintain muscle as you get older.

Protein cycling, then, would mean alternating between those higher amounts on some days and dipping much lower on others. If you lift weights, do regular cardio, or are navigating the muscle-loss reality of midlife, this matters. Your nervous system is probably already processing a lot of decisions about your health. Adding another layer of mathematical precision—calculating your body weight, deciding which days are high and which are low, managing how that feels physically and mentally—that’s real cognitive load.

What Critics Are Actually Pointing Out (And Why They Matter)

Registered Dietitian Cara Harbstreet, MS, RD, has been one of the more vocal voices raising a genuinely important flag: protein cycling doesn’t have sufficient long-term human trial data yet. We have some solid short-term studies. We have cellular markers that look promising. What we don’t have is decades of evidence showing that people who cycle their protein live longer, healthier lives compared to those who maintain consistent intake. That’s a real difference between “interesting science” and “proven strategy.”

She’s also pointed out something that resonates on a mental health level: the approach can feel unnecessarily complex for most people. If you’re already managing dietary choices, tracking workouts, handling stress, and taking care of your family or job, adding a cycling protocol might create more friction than freedom. Some people thrive with structure and novelty. Others find it becomes another source of decision fatigue and shame when they don’t stick to it perfectly. Both reactions are valid. Both are real.

Should You Actually Try This? An Honest Framework

Protein cycling might make sense if you’re already consistently eating adequate protein, you’re fairly active, and you’re genuinely curious about exploring it as an experiment. If you’ve got solid baseline nutrition habits and you want to try something informed by emerging longevity research, that’s reasonable. Track how you feel—your energy, your mood, your strength, your digestion. Notice if alternating protein feels genuinely helpful or if it just becomes stressful.

It probably doesn’t make sense if you’re still working on consistent protein intake in the first place, you’re managing an eating disorder or disordered eating patterns, or your mental health is sensitive to restrictive patterns. The fundamentals matter more than the optimization. Getting enough protein, moving your body regularly, managing stress, sleeping decently—those basics will outperform fancy protocols every time.

Here’s what I keep coming back to: longevity research is genuinely interesting, and it’s okay to follow it without implementing every finding immediately. You don’t have to choose between respecting the science and protecting your peace. The most sustainable approach to aging well isn’t the most complex one—it’s the one you’ll actually maintain while still enjoying your life. Tell me what you’re curious about or what you’ve already tried. The conversation about what actually works for real humans with real lives is just as valuable as the research itself.

Categories
Blog

The Longevity Protocol Revolution: What the Science Actually Shows (and What It Doesn’t)

We’re Measuring Age Wrong. That’s About to Change Everything.

Here’s something that should blow your mind: your chronological age and your biological age might be completely different numbers. You could be 45 years old and have the cellular machinery of a 52-year-old. Or the reverse. And now we can actually measure it.

Epigenetic clocks are one of the most significant breakthroughs in aging research. These tests read patterns of chemical modifications on your DNA—not the genes themselves, but the switches controlling them—to estimate how old your cells actually are. Think of it as your body’s real scorecard. This distinction matters because biological age predicts lifespan, disease risk, and cognitive decline far better than the number of candles you blow out on your birthday.

What makes this revolutionary isn’t just the measurement. It’s that we now have a testable target. You can make a change, wait months, test again, and see if your biological age actually shifted. This transforms longevity from guesswork into an experiment you can run on yourself.

The Zombie Cell Problem—And Why Companies Are Betting Billions on a Solution

Your body accumulates damaged cells that refuse to die. They don’t replicate. They don’t function properly. They just sit there, sending out inflammatory signals that age everything around them. Scientists call them senescent cells. Everyone else calls them zombie cells. And there’s growing evidence they’re a major driver of aging itself.

For years, this was theoretical. Then senolytic drugs emerged—compounds designed to clear these zombie cells out of your system. Early human trials are showing something genuinely promising. Some participants experienced improved physical function, reduced inflammation markers, and better mobility after treatment. This isn’t a cure-all. It’s not even available to most people yet outside clinical settings. But it’s the first time we’ve had a pharmacological intervention that targets a specific mechanism of aging and shown human benefit.

The research is still young. Most studies involve small sample sizes. Long-term safety data doesn’t exist yet. But this is exactly the kind of evidence that’s pushing serious longevity science forward—not the supplement industry’s marketing claims, but actual biological mechanism followed by human testing.

The Protocol Moment We’re In Right Now

You’ve probably heard about Bryan Johnson’s Blueprint protocol. It made headlines because a tech entrepreneur spent an enormous amount of money documenting his personal longevity experiment in obsessive detail. That’s not why it matters. It matters because it represents something real happening in longevity science: the mainstreaming of protocol-based thinking.

Researchers like Peter Attia and Andrew Huberman shifted the conversation from general wellness tips to specific, measurable, testable protocols. Instead of “exercise is good,” the conversation became: What heart rate zones? How many minutes per week? What type of strength training correlates with mortality reduction? This precision-based approach has genuine value. It also comes with real risks if you don’t understand the evidence backing each piece.

This is where things get messy. Because alongside legitimate protocol research, there’s an entire market of compounds getting adopted based on weak evidence or theoretical benefit. NAD+ precursor supplements are a perfect example. The NAD+ market has exploded to over a billion dollars annually. The underlying theory is solid—NAD+ declines with age, and boosting it might restore cellular energy metabolism. But the actual human evidence? Mixed at best. Studies in animals show promise. Human studies show inconsistent results, often with small sample sizes. Yet people are spending significant money on these supplements based largely on promise.

What’s Real Evidence Versus Profitable Speculation

Let’s be direct: caloric restriction works. When you reduce calories, you trigger longevity pathways. Animals live longer. Some human markers improve. The problem is sustainability—most people can’t maintain caloric restriction for decades. So researchers started looking for caloric restriction mimetics: drugs that activate the same pathways without requiring you to eat less. Rapamycin is one example. It’s entering off-label use in longevity circles despite the fact that we have virtually no long-term human data on this application. Some longevity clinics offer it. The theory is sound. The evidence in humans? Honestly, it’s weak.

This matters because there’s a huge gap between “biologically plausible” and “proven to extend human lifespan.” We can only generate human lifespan data through longitudinal studies taking decades, or by using biomarkers as proxies. When someone tells you something extends lifespan, ask which one they’re actually measuring. If it’s animal studies, that’s valuable context but not human proof. If it’s biomarkers, ask which markers and whether those markers actually predict longevity.

My honest read: we’ve made real progress on understanding aging mechanisms. Senolytic drugs are showing early human promise. Epigenetic clocks are actually working. But most longevity interventions still rely on biomarker improvements rather than actual lifespan data. That’s changing as the research accelerates. Stay skeptical of anyone claiming certainty right now.

Where to Actually Direct Your Attention

To engage with this science meaningfully, start by understanding what’s proven versus what’s promising. Follow sources like Lifespan News longevity research that do the work of distinguishing between genuine breakthroughs and marketing. Read the actual studies when possible. Look for human data. When studies exist only in animals or cells, acknowledge what you’re looking at.

The fundamentals still matter most. Sleep quality, consistent strength training, metabolic health, stress management—these aren’t sexy, they aren’t new, and they don’t generate billion-dollar markets. They also have decades of solid human evidence behind them. Build these first, then layer in protocols once your foundation is solid. Longevity Technology covers emerging interventions worth watching as they move through research phases.

Most importantly, remember that longevity science is moving fast. What we think we know keeps changing as better evidence emerges. Stay curious. Ask good questions. And notice when your excitement about a new protocol is coming from genuine understanding versus just really good marketing. The science itself is genuinely exciting without needing exaggeration.

What longevity research is actually making you reconsider your approach? I’d genuinely like to know which studies have shifted your thinking.

Categories
Blog

Beyond the Scale: What Year Two on GLP-1s Really Looks Like for Women

The Cardiovascular Plot Twist Nobody Expected

When you start talking about semaglutide or tirzepatide, the conversation usually lands on weight loss numbers. But here’s where it gets interesting. Recent research out of the SELECT trial published in the New England Journal of Medicine found that semaglutide reduced cardiovascular events by approximately one-fifth in non-diabetic adults with obesity. That’s not a rounding error. That’s a meaningful reduction in heart attacks and strokes, independent of how much weight someone actually lost.

What does this mean for you in year two? Your body is likely experiencing systemic changes that go way beyond what the scale tells you. The medications work on multiple pathways at once. Your cardiovascular system isn’t just benefiting from weight loss alone. The medication itself appears to have direct protective effects on your heart and blood vessels. You can read more about these findings in the NEJM SELECT Trial Results on Semaglutide and Cardiovascular Risk.

Tirzepatide’s Rise and What That Tells Us About Real-World Outcomes

Tirzepatide, marketed as Mounjaro, received FDA approval for chronic weight management in late 2023. By 2025, it’s now the most prescribed branded medication in its entire class across the United States. That’s not because of marketing hype. People are experiencing results, and they’re talking about them. When millions of prescriptions happen, the collective experience matters.

The FDA approval data showed strong efficacy, but real-world use has revealed something else entirely. Women specifically have been reporting that the medication works differently for them than the clinical trial data predicted. You can explore the approval details in the FDA Tirzepatide Approval Information. But the lived experience story is being written by people like you, right now, in year two of treatment.

The Muscle Loss Reality (And How to Actually Address It)

Here’s the number that should make you sit up and pay attention. Research published in Nature Medicine in 2025 found that approximately 40 percent of weight lost on GLP-1 medications includes lean muscle mass. That’s not a small portion. That’s nearly half of your weight loss potentially coming from muscle tissue rather than fat. And this happens without conscious resistance training intervention.

This data completely changed how bariatric surgery specialists approach these medications. The American Society for Metabolic and Bariatric Surgery documented a 28 percent increase in patients specifically asking about muscle preservation protocols because of GLP-1 concerns. Women are walking into their appointments with real questions now. They’re asking about resistance training, protein targets, thinking more carefully about their health outcomes instead of just waiting to see what happens.

The practical implication for year two? If you haven’t prioritized strength training yet, this is your signal. You don’t need to become a bodybuilder. Two to three sessions per week of resistance work, combined with hitting protein targets (generally 0.7 to 1.0 grams per pound of your goal body weight), meaningfully changes what your weight loss actually represents. You’re shifting the ratio of fat loss to muscle preservation in your favor.

The Unexpected Psychological Shifts Nobody Warns You About

Let’s talk about what actually surprised people in year two. Patient-reported outcomes in Obesity Reviews showed that 61 percent of women on semaglutide for 12 months or longer reported unexpected changes in alcohol cravings and food noise reduction. Sixty-one percent. That’s not an outlier experience. That’s the dominant experience.

Food noise is that constant mental chatter about what you’ll eat next, whether you’re hungry, what’s in the kitchen. For many women, it never stops. Until it does. And then it’s genuinely disorienting. Some describe it as the first time they’ve experienced silence in their heads in decades. Others find it unsettling. Some people report that alcohol simply doesn’t appeal to them anymore. A glass of wine they used to enjoy feels completely uninteresting.

These changes matter for year two because you might be navigating social situations differently. You might have more mental space for other things. You might need to rethink how you relate to food around holidays or celebrations. This isn’t inherently good or bad. It’s just real, and it deserves attention.

Thinking Probabilistically About Your Own Outcomes

Here’s the honest truth about the second year on these medications. The data shows general patterns, but your body will write its own story. Twenty percent cardiovascular risk reduction sounds great in population terms, but it means something specific for your individual risk profile. Forty percent muscle loss in weight loss is a statistical reality, but it depends entirely on whether you’re doing resistance training. Sixty-one percent experiencing food noise reduction is meaningful, but that also means 39 percent don’t.

The invitation for you in year two is to stop thinking about these medications in binary terms, whether they work or they don’t, and start thinking statistically. What’s your actual adherence? Are you doing the resistance training? What does your protein intake look like? How is your cardiovascular health actually trending? Are the psychological shifts beneficial for you or something to work through with professional support?

This is where individualized medicine happens. You have access to more data and more research than ever before. Your doctor has more information. And you have the lived experience nobody else can contribute to your care plan. Year two is where the real optimization happens, where you stop just taking the medication and start actively participating in what that medication is actually doing to and for your body. That’s where the conversation gets interesting.

Categories
Blog

Cortisol Face, Explained: Why Social Media Numbers Don’t Equal Medical Facts

The Trend That Captured 2.1 Billion Views (And Your Worry)

Your face feels puffy. You gained a few pounds. You’re tired more than usual. Then you see a TikTok creator explaining that your face is literally showing your cortisol levels—and suddenly, your symptoms have a name, a cause, and a solution you can buy.

Cortisol Face, Explained: Why Social Media Numbers Don't Equal Medical Facts
Cortisol Face, Explained: Why Social Media Numbers Don’t Equal Medical Facts

The hashtag #cortisolface has amassed over 2.1 billion views on TikTok as of early 2026. That’s not a typo. Creators across the platform are building entire followings around the idea that puffiness, weight gain, acne, and fatigue are all visual signatures of chronically elevated cortisol. The message is consistent: your body is broken, your hormones are broken, and they have the supplement or wellness protocol that fixes it.

Here’s what we need to talk about: the view count doesn’t make the science true. And the science matters more than you might think.

Illustration for Cortisol Face, Explained: Why Social Media Numbers Don't Equal Medical Facts
Illustration for Cortisol Face, Explained: Why Social Media Numbers Don’t Equal Medical Facts

What Doctors Actually Know About Real Cortisol Problems

Let’s start with the actual condition the internet is obsessing over: Cushing’s syndrome, which is genuine hypercortisolism. This is a real disease. It destroys bone density, causes severe muscle weakness, induces depression, and creates the facial puffiness everyone keeps filming. It’s also extraordinarily rare.

The Endocrine Society released a clinical statement in 2025 clarifying the numbers. True hypercortisolism affects 10 to 15 people per million annually. In the United States, that means approximately 3,300 to 5,000 people get diagnosed each year. To put it in perspective: you are more likely to be struck by lightning in your lifetime than to develop Cushing’s syndrome. Diagnosis requires blood tests, urine tests, imaging studies, and clinical evaluation by an endocrinologist—not a selfie assessment and a TikTok comment section consensus.

The problem is that the symptoms social media attributes to “cortisol face” are real. Puffiness exists. Weight gain happens. Fatigue is legitimate. But these symptoms have dozens of causes: thyroid dysfunction, sleep deprivation, dietary sodium intake, medications, hormonal cycles, actual stress, autoimmune conditions, and yes, sometimes genuinely elevated cortisol from diagnosable illness. The internet’s move is to skip the diagnostic work and assume the worst.

For detailed, physician-reviewed information about how cortisol actually functions in your body, The Endocrine Society Patient Resources on Cortisol breaks down the science without the sales pitch.

The Self-Diagnosis Epidemic Nobody Expected

A 2025 survey by the American Psychological Association found that 41 percent of Gen Z adults reported self-diagnosing a cortisol-related condition based on social media content. Let that number sit for a moment. Four out of every ten young adults have convinced themselves they have a hormone disorder they learned about on an app designed to keep them scrolling.

This isn’t a judgment. It’s a pattern. When you see thousands of people describing symptoms that overlap with your own experience, and they’re all pointing to one explanation, your brain does what it’s supposed to do: it looks for patterns, finds meaning, and says “Oh. That’s what’s wrong with me.”

The issue is that pattern-matching isn’t diagnosis. And diagnosis is the difference between targeted treatment and expensive placebo.

The American Psychological Association Stress in America 2025 research shows that while stress is genuinely affecting young adults’ health, the solution isn’t always a supplement. Sometimes it’s sleep. Sometimes it’s reducing actual stressors. Sometimes it’s therapy. But the internet wants to sell you ashwagandha.

The Supplement Boom Isn’t Based on What You Think It Is

Ashwagandha supplement sales in the United States grew 67 percent between 2024 and 2025, according to market data from SPINS. That’s explosive growth driven almost entirely by marketing claims that ashwagandha reduces cortisol and solves “cortisol face.”

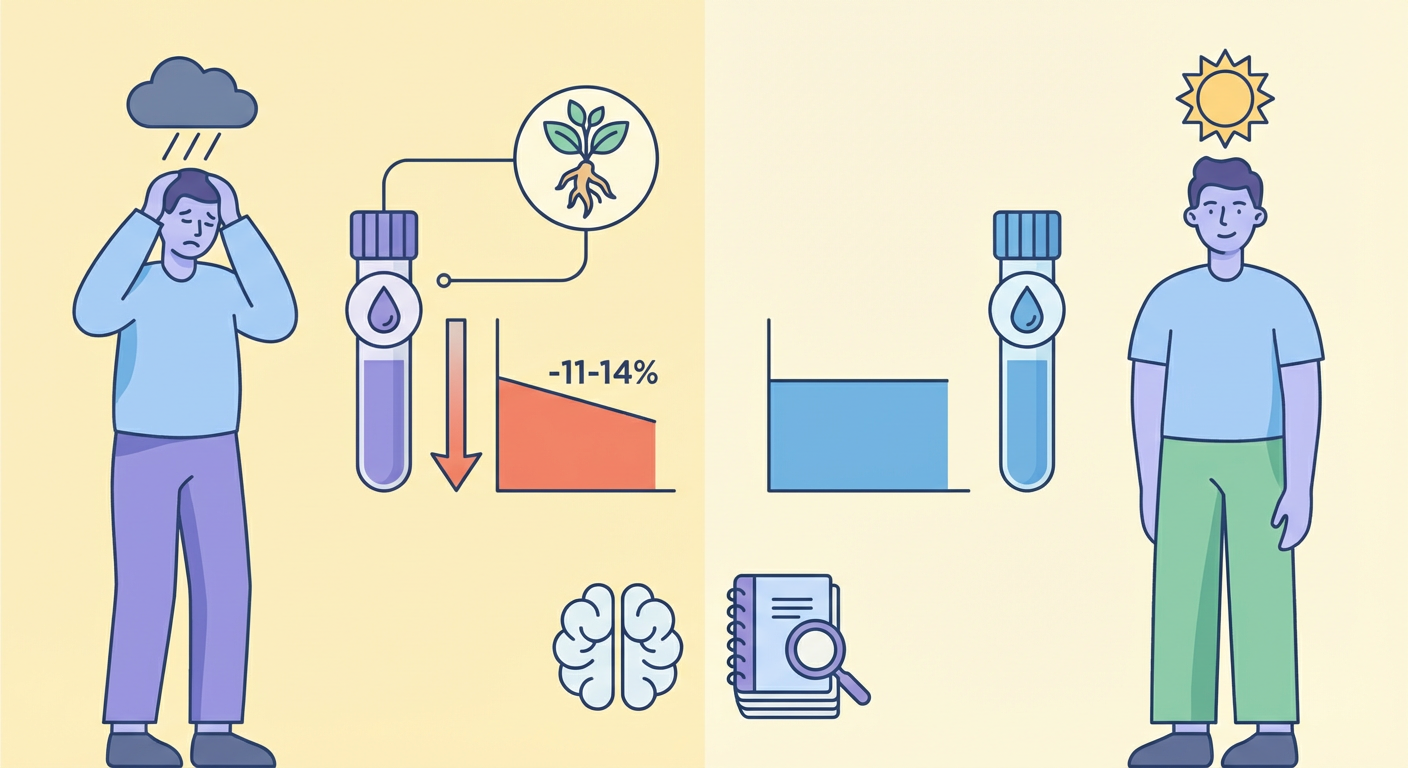
Here’s what the actual research says. A 2025 meta-analysis published in Psychoneuroendocrinology reviewed 28 studies on ashwagandha and cortisol. The results: the supplement produced statistically modest reductions in salivary cortisol, averaging 11 to 14 percent, but only in clinically stressed populations—people already diagnosed with stress-related conditions. In healthy individuals with baseline cortisol levels, ashwagandha showed no significant effect.

Translation: if you’re already dealing with clinical stress and you’re looking for an 11 to 14 percent reduction, ashwagandha might help. If you’re a healthy person who thinks your puffy face means you have a hormone disorder, a supplement won’t fix something that probably isn’t broken. And it might cost you $25 to $50 per bottle to find that out.

The real kicker? That 11 to 14 percent reduction is comparable to what you get from consistent sleep, regular movement, and actual stress reduction. Those cost nothing except intention.

What to Do When You’re Genuinely Concerned

If you’re experiencing unexplained weight gain, persistent fatigue, or facial puffiness that concerns you, don’t ignore it. Your body is communicating something. But don’t skip straight to self-diagnosis either.

Talk to your primary care doctor. Describe what you’re observing. Request basic blood work if it seems appropriate. Get your thyroid checked. Ask about your sleep quality. Discuss your actual stress levels and whether they’ve changed. Let someone with training and diagnostic tools do the assessment.

If your doctor suspects a cortisol-related condition, they’ll refer you to an endocrinologist. That person will order the right tests. You’ll get an actual answer instead of a TikTok answer. That answer might be “you’re fine” or “here’s what we found and here’s how we treat it.” Either way, you’ll know.

What won’t happen? Diagnosis by algorithm. Treatment by trend. Or paying for supplements that don’t address the real issue.

The numbers are real. Your symptoms are real. But the connection TikTok is drawing between them might not be. If you’re noticing changes in your body or your health, that’s worth investigating—just do it with someone qualified to actually investigate. What’s been your experience with health trends online? Have you found ways to distinguish between real information and marketing? I’d genuinely like to hear what’s worked for you.